

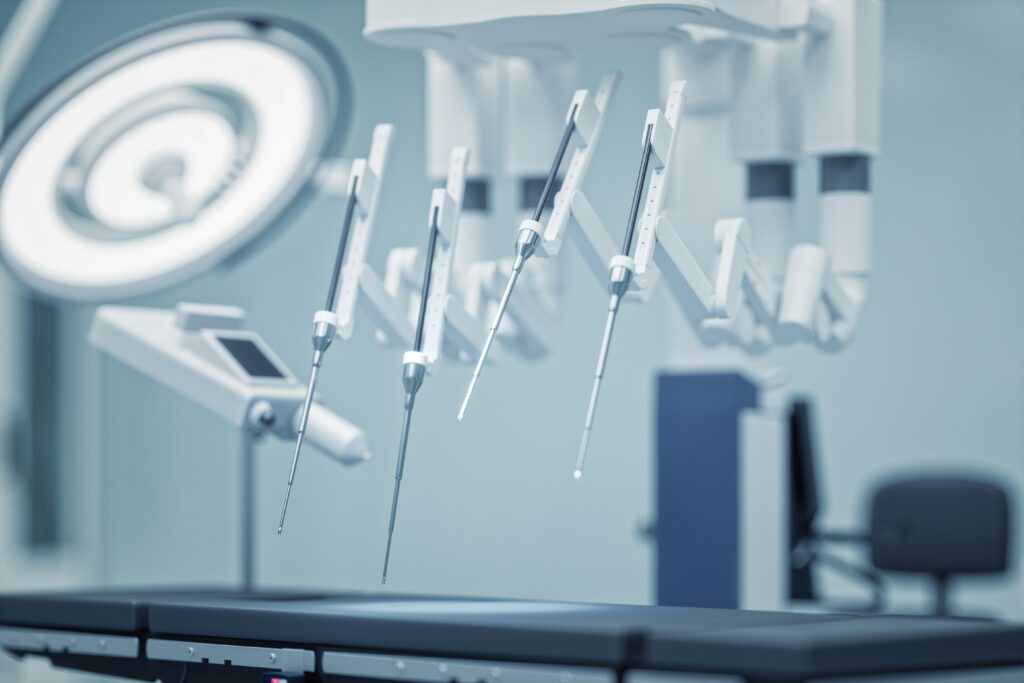

When King Faisal Specialist Hospital and Research Centre (KFSH) in Riyadh talks about robotic surgery, it is not selling gadgets in the operating theatre; it is selling a new architecturefor complex care. That distinction matters for Scotland, because we are in danger of treating robots as an endpoint rather than a starting point.
KFSH has turned robotics into a system design choice, not a bolt‑on upgrade. Its world‑first fully robotic heart and liver transplants, and advanced oncologic and neurological procedures, are framed as validation of a broader model in which precision, data and minimally invasive techniques are embedded across specialties. The real story is not the headline surgeries; it is that robotics sits inside routine workflows, training and governance as the default way to deliver predictable outcomes at volume.
Scotland, by contrast, is in the midst of a quieter, more incremental experiment: what happens when a small, publicly funded health system tries to make robotics normal rather than novel. Since 2021, more than 10,000 patients across Scotland have benefitted from da Vinci robotic‑assisted surgery (RAS), after a major Scottish Government expansion that added 12 systems and more than tripled the installed base. Earlier, ministers had invested around £19.8m in 10 surgical robots, taking the national fleet to 13 and targeting high‑open‑surgery specialties such as bowel, urology and gynaecology. This is now baked into the Scottish Cancer Action Plan 2023–26 as a key lever for better outcomes, equity of access and productivity.
Robots are the wedge, not the story
KFSH’s framing is useful because it strips away the fetish around the robot itself. Hardware is just a wedge that forces deeper decisions: what data you capture, how you train, and how you redesign pathways when length of stay collapses from a week to a day. In Riyadh, those decisions sit inside a national agenda – Saudi Vision 2030 – that couples capital with a deliberate push to be seen as a global health innovation hub.
Scotland does not have that scale or liquidity, but it does have a compact system, a dense university base and an emerging digital health and med‑tech community. The risk is that robots are treated as the destination – a success in procurement terms – rather than as the forcing function for the next layer: AI‑enabled decision support, surgical analytics and new models of follow‑up and rehab.
If KFSH is building the “Davos case study” of robotic medicine, Scotland has an opportunity to build the “small‑nation operating system” – showing how you turn a finite number of platforms into a learning network that punches above its weight. That only happens if the conversation moves decisively beyond where the robots sit and which specialty gets them next.
Where AI should already be in the room
Read KFSH’s narrative closely and you see the outline of an AI‑centric future, even when it is not foregrounded. Once procedures are highly standardised and instrumented, the next differentiator is how you: model risk pre‑operatively, optimise intra‑operative choices, and predict recovery trajectories and complications.
That is all AI territory. Robotic platforms, by design, generate rich structured data and imaging. Scotland is already producing that raw material: thousands of RAS cases across multiple boards, focused initially on colorectal and gynaecology with expansion into urology, thoracic and head and neck surgery. The question is whether that data is treated as exhaust, or as fuel for a new wave of AI products and services.
A national robotic surgery “data spine” – standardising capture across systems and sites – would give Scotland a single, de‑identified dataset for benchmarking, quality improvement and algorithm development. Boards like NHS Forth Valley, now introducing RAS with fresh funding, could design AI‑ready workflows from day one: structured fields, consistent imaging capture and shared outcome measures across the network. And training should evolve from “how to use the robot safely” to “how to work with AI tools critically,” so surgeons become informed users of algorithms, not just operators of machines.
An ecosystem problem, not just an NHS problem
It is tempting to see all of this as an NHS problem: more capital, better IT, updated curricula. But the leverage sits at ecosystem level. Universities get a live testbed for applied AI in surgery; startups get specific problems to solve, from list optimisation and bed planning to AI‑guided rehab; larger tech and med‑tech players get a contained environment for serious pilots rather than perpetual “innovation theatre.”
Meanwhile, policymakers can use the spread of robotics as a line in the sand: if public money buys advanced platforms, common data standards and responsible reuse for innovation should be the default expectation, not an optional extra. That demands clarity on governance, IP and consent, but if it is not tackled now, Scotland will end up with a modern hardware estate and no enduring strategic asset.
KFSH will stand on global stages and present robotics as part of a precision‑care architecture that aligns clinical excellence with scalability. Scotland’s story is still being written; whether it becomes a reference model for small‑nation, AI‑enabled robotic surgery depends less on the robots themselves, and more on what the ecosystem chooses to build around them.























